


Postpartum Melasma: A 6–8 Week Plan Built Around Tinted SPF
Photoprotection with a tinted, iron-oxide sunscreen and pregnancy-safe topicals like azelaic acid or niacinamide are the correct first move for postpartum melasma. Results are typically checked at 6 to 8 weeks. Strong agents like hydroquinone and tretinoin work faster but are off-limits during pregnancy and need clinician supervision once you’re cleared to use them. If pigment hasn’t budged after two months of consistent care, that’s your signal to book a dermatologist visit rather than escalate on your own.
TL;DR:
- Melasma often persists beyond six to eight weeks of protective measures, especially in women with medium to darker skin tones who experience more stubborn pigmentation.
- Ongoing triggers such as sunlight, visible light, genetics, heat, and certain medications can cause recurrent melasma flares despite treatment efforts.
- Topical treatments like azelaic acid or niacinamide are safe and effective initial options postpartum, while agents like hydroquinone or tretinoin require dermatologist supervision.
- Procedural treatments carry risks of post-inflammatory hyperpigmentation and should only be considered after the skin and pigment are stabilized.
- Maintenance routines with tranexamic acid peptides, barrier support, and consistent tinted SPF help prevent relapse, but persistent pigmentation may still require professional management.
Table of Contents
- What Postpartum Melasma Looks Like and How to Recognize It
- Why Pregnancy Triggers It and What Keeps It Coming Back
- Does Postpartum Melasma Actually Fade on Its Own?
- What’s Actually Safe to Use Right Now
- Procedures Postpartum: Peels, Microneedling, and Lasers
- A Simple Phased Plan You Can Follow
- When It’s Time to Call a Dermatologist
- How Cellure Fits Into Long-Term Pigment Maintenance
- What I’d Tell a Friend Going Through This
- Where to Start With Cellure’s Maintenance Serums
- Sources
- FAQ
What Postpartum Melasma Looks Like and How to Recognize It
Melasma shows up as symmetric brown or gray-brown patches, usually across the cheeks, upper lip, forehead, or nose bridge. It’s earned the nickname “mask of pregnancy” for a reason: the pattern is remarkably consistent from one patient to the next.
A few things determine how it presents and how it should be treated.
- Skin tone matters. Melasma is more common and often more stubborn in medium to darker skin tones (Fitzpatrick III through VI), and treatment intensity has to be calibrated accordingly to avoid triggering new dark spots.
- Distribution is diagnostic. Dermatologists look at whether pigment follows a centrofacial, malar, or mandibular pattern, since that helps rule out other causes like post-inflammatory hyperpigmentation.
- A Wood lamp exam can help a clinician determine how deep the pigment sits, which affects which treatments will actually reach it.
If your pigmentation looks asymmetric, appeared after an injury or breakout, or doesn’t fit the classic facial pattern, it may be something other than melasma worth a proper exam before you start treating it as such.
Why Pregnancy Triggers It and What Keeps It Coming Back
Pregnancy floods your system with estrogen and progesterone, and both hormones ramp up melanocyte activity, the pigment-producing cells in your skin. That’s the initial spark. What keeps melasma smoldering after delivery is a mix of ongoing triggers:
- Sunlight and visible light. UV rays are the obvious culprit, but visible light, including the blue light from screens, also stimulates pigment production, which is why standard sunscreens often underperform.
- Genetics. A family history of melasma raises your own risk substantially.
- Heat and certain medications. Photosensitizing drugs and hormonal contraception can both reactivate pigment.
Iron-oxide tinted sunscreens specifically block visible light in a way that plain mineral or chemical filters don’t, and clinical reviews link that added protection to fewer relapses. Many women see real fading over several months postpartum as hormones settle, but relapse is common enough that dermatologists treat melasma as a condition you manage, not one you cure once and forget.
Does Postpartum Melasma Actually Fade on Its Own?
Sometimes, yes. As estrogen and progesterone levels normalize after delivery, some women see noticeable lightening over a few months with nothing more than diligent sun protection. Others find the pigment settles in and barely moves without active treatment.
What separates the two groups isn’t always clear, but darker skin tone, longer sun exposure without tinted protection, and a strong genetic predisposition all tend to predict a more persistent course. Because melasma is fundamentally chronic and relapsing, the realistic goal is control rather than a permanent fix. Think of it less like healing a wound and more like managing a condition that flares under the wrong conditions and stays quiet under the right ones. That reframe matters, because it changes what “working” looks like: fewer flares, lighter patches, and a routine you can sustain, not a single treatment that erases the problem for good.
What’s Actually Safe to Use Right Now
Your first priority is photoprotection, and it needs to be more deliberate than what you might have used before pregnancy. A broad-spectrum sunscreen rated SPF 30 to 50, reapplied every two hours during sun exposure, is the baseline. Choose a tinted formula with iron oxides specifically, since visible light protection is what separates a melasma-appropriate sunscreen from a generic one.
From there, a stepwise approach works best:
- Start with azelaic acid or niacinamide. Both have favorable safety profiles for pregnancy and breastfeeding and are reasonable to begin as soon as you’re cleared for topical treatment. Expect gradual change over several weeks, not overnight results.
- Consider cysteamine as another gentler option if azelaic acid or niacinamide alone isn’t cutting it, though it can be irritating for sensitive postpartum skin and should be introduced slowly.
- Reserve hydroquinone and tretinoin for clinician-supervised use. These remain among the most effective induction agents for melasma, but both are contraindicated during pregnancy, and postpartum use, especially while breastfeeding, should happen under a dermatologist’s guidance in a short, defined course rather than indefinitely.
- Ask about oral tranexamic acid for refractory cases. This is a different animal from topical tranexamic acid. Oral TXA can meaningfully improve stubborn melasma, but it requires screening for thrombosis risk beforehand and is never used during pregnancy.
Pro Tip: Apply your brightening serum to fully dry skin before sunscreen, and give it a full minute to absorb. Layering it onto damp skin dilutes the active ingredient and slows down how evenly it penetrates.
Procedures Postpartum: Peels, Microneedling, and Lasers
Once your topical routine is established and hormones have had time to settle, some women consider procedural add-ons. Superficial chemical peels and microneedling can help with epidermal-dominant melasma, meaning pigment sitting closer to the skin’s surface rather than deep in the dermis.
That said, procedures carry real risk here, and it’s worth being cautious rather than eager:
- Post-inflammatory hyperpigmentation (PIH) is the main danger, especially for medium to darker skin tones, where aggressive treatment can trigger new dark patches worse than the original melasma.
- Energy-based devices, including certain lasers, can cause rebound pigmentation if settings are too aggressive or the treatment is timed poorly.
- Timing matters. Most dermatologists recommend waiting until hormones have stabilized and your topical regimen is optimized before adding any procedure to the mix.
If you do pursue a procedure, an experienced practitioner using conservative settings is non-negotiable, and it should always sit on top of, not instead of, consistent photoprotection.
A Simple Phased Plan You Can Follow
Structure removes a lot of the guesswork here, and it gives you and your dermatologist a shared reference point.
- Weeks 0 to 6: Commit to daily tinted sunscreen, start a pregnancy-and-breastfeeding-safe topical (azelaic acid or niacinamide), skip harsh exfoliants or unproven “natural remedies for melasma” that can irritate healing postpartum skin, and take a photo under consistent lighting each week to track change.
- Week 6 to 8 review: Compare your photos. If improvement is under roughly 30 percent, this is the point to discuss escalation with your provider, whether that’s a short supervised course of hydroquinone, oral TXA after proper screening, or a conservative procedure.
- Maintenance phase: Once pigment has visibly improved, taper toward gentler, non-phenolic brighteners like niacinamide or azelaic acid, and keep tinted SPF as a permanent daily habit rather than a temporary fix.
Pro Tip: Keep your progress photos in one folder with dates in the filename. Six weeks feels slow day to day, but a side-by-side comparison usually reveals more change than you’d notice in the mirror.
When It’s Time to Call a Dermatologist
Persistent pigmentation past the 8-week mark, an uncertain diagnosis, or a bad reaction to any product you’ve tried are all solid reasons to get a professional opinion rather than keep experimenting alone.
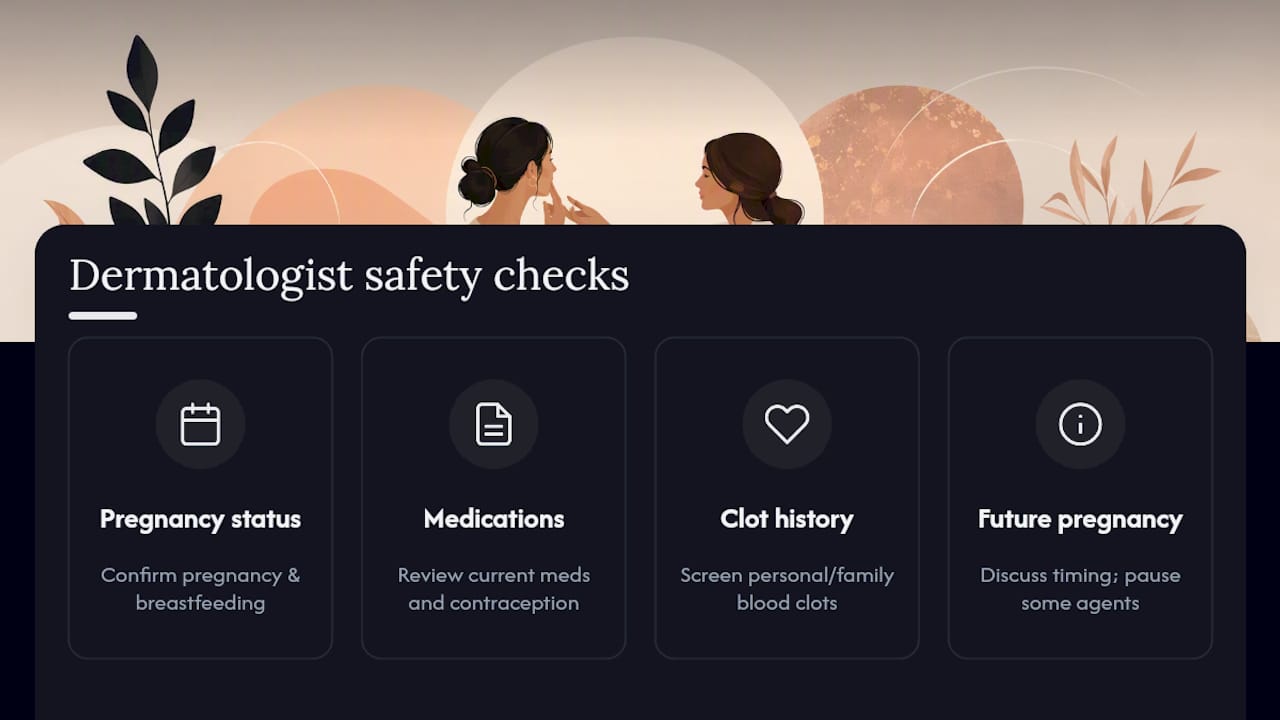
Before prescribing certain treatments, a dermatologist will typically run through a few safety checks: confirming your pregnancy and breastfeeding status, reviewing current medications including contraception, and, if oral tranexamic acid is on the table, screening for personal or family history of blood clots. It’s also worth asking how any treatment plan fits with future pregnancy plans, since some agents need to be paused well in advance.
How Cellure Fits Into Long-Term Pigment Maintenance
Once active treatment has brought pigment under control, maintenance is what keeps it that way. Cellure’s tranexamic acid peptide serum is formulated to support even tone alongside peptides that reinforce the skin barrier, a combination suited to the “hold steady” phase after induction therapy, rather than the acute flare itself.
A maintenance routine generally covers three things at once:
- Brightening support from tranexamic acid and complementary actives, used consistently rather than as a quick fix.
- Barrier repair, since postpartum skin is often more reactive and needs support to tolerate active ingredients without irritation.
- Antioxidant and peptide input that helps guard against the kind of low-grade inflammation that can reignite pigment.
None of this replaces a clinician’s judgment. If you’re breastfeeding, confirm any new product with your provider first, and never layer these serums on top of an unmonitored prescription bleaching agent without checking that the combination is actually safe.
What I’d Tell a Friend Going Through This
Melasma after pregnancy is genuinely disheartening, especially when you’re already adjusting to a body and face that don’t quite match what you remember. That frustration is valid, and it doesn’t mean you’re doing anything wrong.
What actually moves the needle is unglamorous: sunscreen you reapply without fail, a gentle topical you stick with for weeks rather than days, and a follow-up plan instead of guessing. Consistency, not intensity, is what gets you there.
— Sara
Where to Start With Cellure’s Maintenance Serums
Once your dermatologist has you past the active treatment phase, the question becomes what keeps pigment from creeping back. Cellure’s best-sellers collection covers three formulas built for exactly that stretch of the process, each priced at $60.
One serum targets uneven tone directly, pairing tranexamic acid with peptides for ongoing brightening support. Another focuses on barrier repair and hydration, which matters because postpartum skin tends to run more reactive and needs reinforcement before it can tolerate active ingredients well. A third supports skin firmness and volume, addressing the broader postpartum skin changes that often show up alongside pigmentation.
A simple starter routine: gentle cleanser, your chosen brightening serum, then tinted SPF every morning without exception. Browse the full lineup on Cellure’s site and build a routine around whichever serum matches where you are in your maintenance phase.
This article is general information, not a substitute for advice from a qualified doctor. Consult a qualified healthcare professional about your own circumstances before acting on anything here.
Sources
- Photoprotection and visible light in melasma (PMC9790748)
- Melasma review and management (StatPearls / NCBI Bookshelf)
- Latin American consensus on the treatment of melasma (PubMed 39415312)
- Update on Melasma—Part II: Treatment (PMC9464276)
FAQ
Does postpartum melasma go away on its own?
For some women, pigment fades noticeably over several months as hormones normalize, particularly with strict daily sun protection. For others it persists and requires active topical treatment, and because melasma is chronic and relapse-prone, ongoing maintenance is usually the realistic goal rather than a one-time cure.
What are the symptoms of a postpartum hormone crash?
A postpartum hormone crash typically brings fatigue, mood swings, night sweats, and hair shedding as estrogen and progesterone drop sharply after delivery. Skin changes, including melasma flares or new breakouts, often track alongside these hormonal shifts rather than occurring independently.
Is it normal to have acne nine months after giving birth?
Yes, hormonal fluctuations can continue well past the immediate postpartum period, especially if you’re breastfeeding or have resumed a menstrual cycle. Acne and melasma frequently overlap during this stretch since both are driven by shifting estrogen and progesterone levels.
Will hormonal melasma go away eventually?
It can improve substantially once hormone levels stabilize, but many women see it return with sun exposure, heat, or future hormonal changes like contraception or another pregnancy. Consistent tinted photoprotection and a maintenance topical routine, such as Cellure’s tranexamic acid peptide serum alongside daily SPF, are the most reliable ways to keep it under control long term.